MRCS
MRCS Part B OSCE: stations, skills and spoken examination
The OSCE shape, the station families and what they reward, spoken technique that transfers to interviews, and a preparation plan.
By the TheatrePass editorial team · updated 1 September 2026 · 4 min read
Part B is where MRCS stops being a reading exercise. It is a circuit of observed, timed, spoken stations, and candidates who sailed through Part A regularly stumble here because they prepared silently for an examination that happens out loud. This guide covers the OSCE shape, the station families and what each rewards, the spoken technique that transfers directly to selection interviews, and a preparation plan.
The shape of the OSCE
Part B is an objective structured clinical examination: a circuit of short stations sampling two broad areas, applied knowledge (anatomy, surgical pathology, applied science) and applied skills (history taking, clinical examination, procedural skills and communication). Station counts, timings and weightings are set by the colleges and have changed before, so take the current intercollegiate guidance as the only authoritative description and treat everything else, including this guide, as pattern. Whatever the exact circuit, the constant is that you are scored in real time on what you say and do, not on what you know.
The station families and what they reward
Anatomy and applied knowledge
These are viva-style stations: a prosection, an image or a scenario, then structured spoken questioning. The technique is classification first (give your answer as spoken headings), relate every structure to a clinical consequence, and say what you safely know rather than free-associating. Silence is not the main danger; unstructured talking is. Practise with a colleague holding the atlas: they point, you classify aloud, thirty minutes at a time.
History and examination
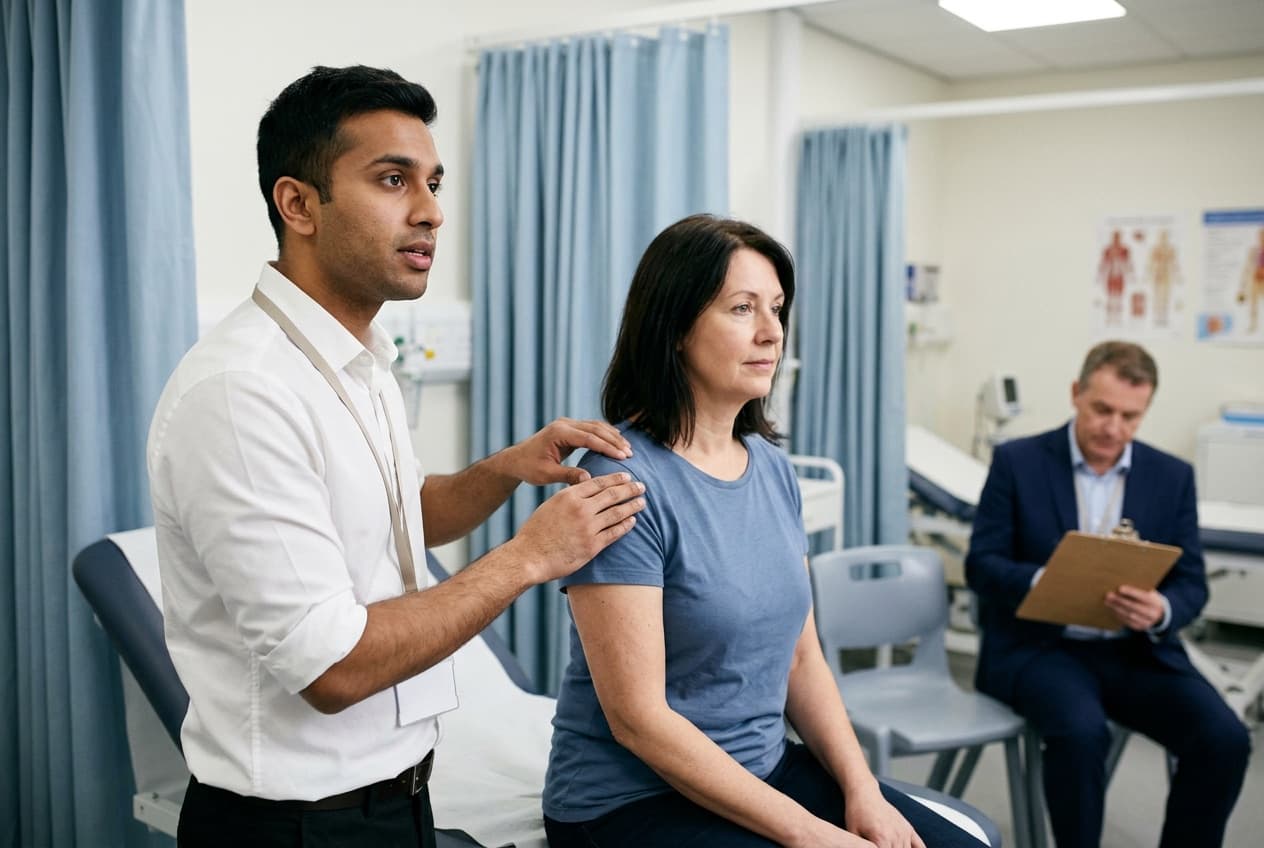
Practised routines win: a focused surgical history with a visible structure, examinations rehearsed until smooth, findings summarised in two sentences with a differential and a plan. Signpost as you go, because the examiner can only score what they can follow. Time the routines weekly; smoothness under a clock is a different skill from smoothness without one.
Communication and procedure
Consent conversations, explaining a diagnosis or an operation, structured handovers and core procedural skills. The scoring spirit is the same as selection interviews: clarity, safety, empathy and structure under time pressure. Write short frameworks for the recurring conversations (consent, complication, refusal) and rehearse them until the structure survives an upset role-player.
The technique that transfers to interviews
Part B rehearsal is interview rehearsal wearing a different badge. Both reward an answer with a spoken spine, explicit safety language, composure under redirection, and the habit of finishing inside the time. Candidates who prepare Part B aloud arrive at core and specialty interviews with the hardest skill already built: thinking in organised speech while someone watches.
What examiners reward
- A spoken structure announced and then followed; examiners mark against criteria, and structure makes the criteria easy to award.
- Safety said aloud: the contraindication checked, the consent confirmed, the senior named.
- Composure when redirected; the follow-up question is an invitation, not an ambush.
- Honest limits: a clean statement of what you would look up or escalate scores better than confident invention.
- Finishing inside the time with a summary sentence rather than trailing off.
Knowledge into speech
The gap between knowing and saying is mechanical, and it closes with repetitions. Take any topic you have just revised and give it sixty seconds of structured speech: definition, classification, clinical relevance, safety point. Do this from the first week of preparation, ten times a week, and the viva stations stop being frightening, because nothing in them will be happening for the first time.
A preparation plan
- 1Weeks 10 to 8: consolidate aloudRevise anatomy and applied knowledge by speaking it: classify structures and answer past-style prompts out loud from the first week.
- 2Weeks 8 to 4: build circuitsPractise station-length blocks with colleagues: one examines, one performs, one scores against a simple checklist. Examine real patients on the wards whenever the chance appears. Rotate roles deliberately; examining a colleague teaches you what examiners need to hear.
- 3Weeks 4 to 1: simulateFull timed circuits, communication scenarios with someone unfamiliar where possible, and review of recordings for structure, pace and safety language.
- 4Final days: light and familiarKnown routines only, short daily voice work, logistics sorted, sleep protected.
Common mistakes
- Silent revision for a spoken examination.
- Treating communication stations as soft and unpreparable; they are scored, structured and rehearsable.
- Examination routines never run against a clock until the day itself.
- Collapsing at the first redirection because every practice run was uninterrupted.
- Knowledge revised to Part A depth but never reorganised for spoken retrieval.
How TheatrePass helps
The core skill Part B examines, structured clinical speech under observation, is exactly what TheatrePass mock interviews train: timed spoken answers, follow-up questioning and feedback on structure and safety language. Candidates preparing for Part B and a selection interview in the same season are building one skill, and rehearsing it aloud is the whole method.
Interview formats and selection criteria change between recruitment cycles. Content is reviewed each cycle and dated; always confirm details against the current national recruitment guidance.